
Home / About LSDs / Mucopolysaccharidosis (MPS)
Mucopolysaccharidosis (MPS): Types, Symptoms and Treatment in India
MPS is short for mucopolysaccharidosis, a group of rare inherited disorders in which complex sugars build up in the bones, joints, organs and, in some types, the brain. Treatment is available for several types, and early diagnosis matters.
Key facts
Cause
Deficiency of one of the enzymes that break down glycosaminoglycans (GAGs)
Inheritance
Autosomal recessive, except MPS II, which is X-linked
Mainly affects
Bones, joints, heart, airways, eyes, ears and, in some types, the brain
How common
About 1 in 25,000 births for all types together
Treatment
ERT for MPS I, II, IVA, VI and VII; stem cell transplant for some
LSDSS community
140+ registered MPS families across India
Overview
What is mucopolysaccharidosis?
Mucopolysaccharidoses are a group of inherited lysosomal storage disorders. People with MPS lack, or have too little of, one of the enzymes needed to break down long chains of sugar molecules called glycosaminoglycans (GAGs), once called mucopolysaccharides.
GAGs then build up in cells, blood and connective tissue throughout the body. This causes progressive damage to the skeleton, joints, heart, airways, eyes, ears, liver and spleen and, in some types, the brain.
There are seven main types, each caused by a different missing enzyme. Most children appear healthy at birth and develop symptoms in the first few years of life.
Video: MPS type I (Hurler, Hurler-Scheie and Scheie syndromes) explained (credit: Osmosis)
MPS in India
MPS is one of the more commonly diagnosed groups of lysosomal storage disorders in India, but many children are still diagnosed late. Early signs such as frequent colds and ear infections, noisy breathing, a hernia or stiff joints are often treated separately for years before the cause is found.
Five types of MPS can now be treated with ERT, and some children benefit from a stem cell transplant if it is done early. A diagnosis also helps families get genetic counselling and plan future pregnancies.
Did you know?
Five types of MPS now have an approved enzyme replacement therapy.
They are MPS I, II, IVA, VI and VII. Research into treatments for the other types, including gene therapy, is under way.
Types of MPS
Each type is caused by a different missing enzyme. Symptoms and severity vary widely, even within the same type.
MPS I (Hurler, Hurler-Scheie and Scheie syndromes)
Caused by a deficiency of alpha-L-iduronidase. The severe form (Hurler syndrome) causes developmental decline, coarse facial features, clouded corneas, and heart and airway problems in early childhood. Milder forms progress more slowly and may not affect learning.
MPS II (Hunter syndrome)
Caused by a deficiency of iduronate-2-sulfatase. It is X-linked, so it mainly affects boys. It causes airway obstruction, joint stiffness, heart disease and, in most patients, a decline in learning and behaviour.
MPS III (Sanfilippo syndrome)
Has four subtypes (A to D). It mainly affects the brain, causing developmental delay, hyperactivity, sleep problems and loss of skills, with milder physical signs.
MPS IV (Morquio syndrome)
Has two subtypes, A and B. It mainly affects the skeleton, causing short stature, knock knees, a short neck and very loose joints. Intelligence is usually normal. Instability of the neck bones can press on the spinal cord.
MPS VI (Maroteaux-Lamy syndrome)
Caused by a deficiency of arylsulfatase B. Intelligence is usually normal, but children develop short stature, stiff joints, clouded corneas, and heart and airway problems.
MPS VII (Sly syndrome)
One of the rarest types, caused by a deficiency of beta-glucuronidase. Severity ranges from a life-threatening form before birth (hydrops fetalis) to milder forms with a range of physical and learning problems.
Related conditions
Mucolipidosis II and III (I-cell disease)
Mucolipidosis II (ML II, also called I-cell disease) and mucolipidosis III (ML III, also called pseudo-Hurler polydystrophy) are rare inherited disorders with many features in common with MPS. They are caused by changes in the GNPTAB gene or, in one form of ML III, the GNPTG gene. These genes are needed to send many enzymes to the lysosomes, so several substances build up at once.
ML II is the more severe form. Signs are often present at birth or in the first months of life, including coarse facial features, thickened gums, stiff joints, bone changes, slow growth, developmental delay, and heart and breathing problems. Most children live only into early childhood.
ML III is milder and usually starts around 3 years of age, with stiff joints, short stature, hip and spine problems and heart valve disease. Learning is often normal or only mildly affected, and many people live into adulthood.
At a glance
Cause
Changes in the GNPTAB or GNPTG gene, which stop many enzymes reaching the lysosomes
Inheritance
Autosomal recessive
How it is diagnosed
Blood tests show very high levels of several lysosomal enzymes; a genetic test confirms it
Treatment
No approved treatment yet. Supportive, orthopaedic and heart care. Stem cell transplants have been tried in ML II, with limited benefit.
Signs and symptoms
Symptoms of MPS
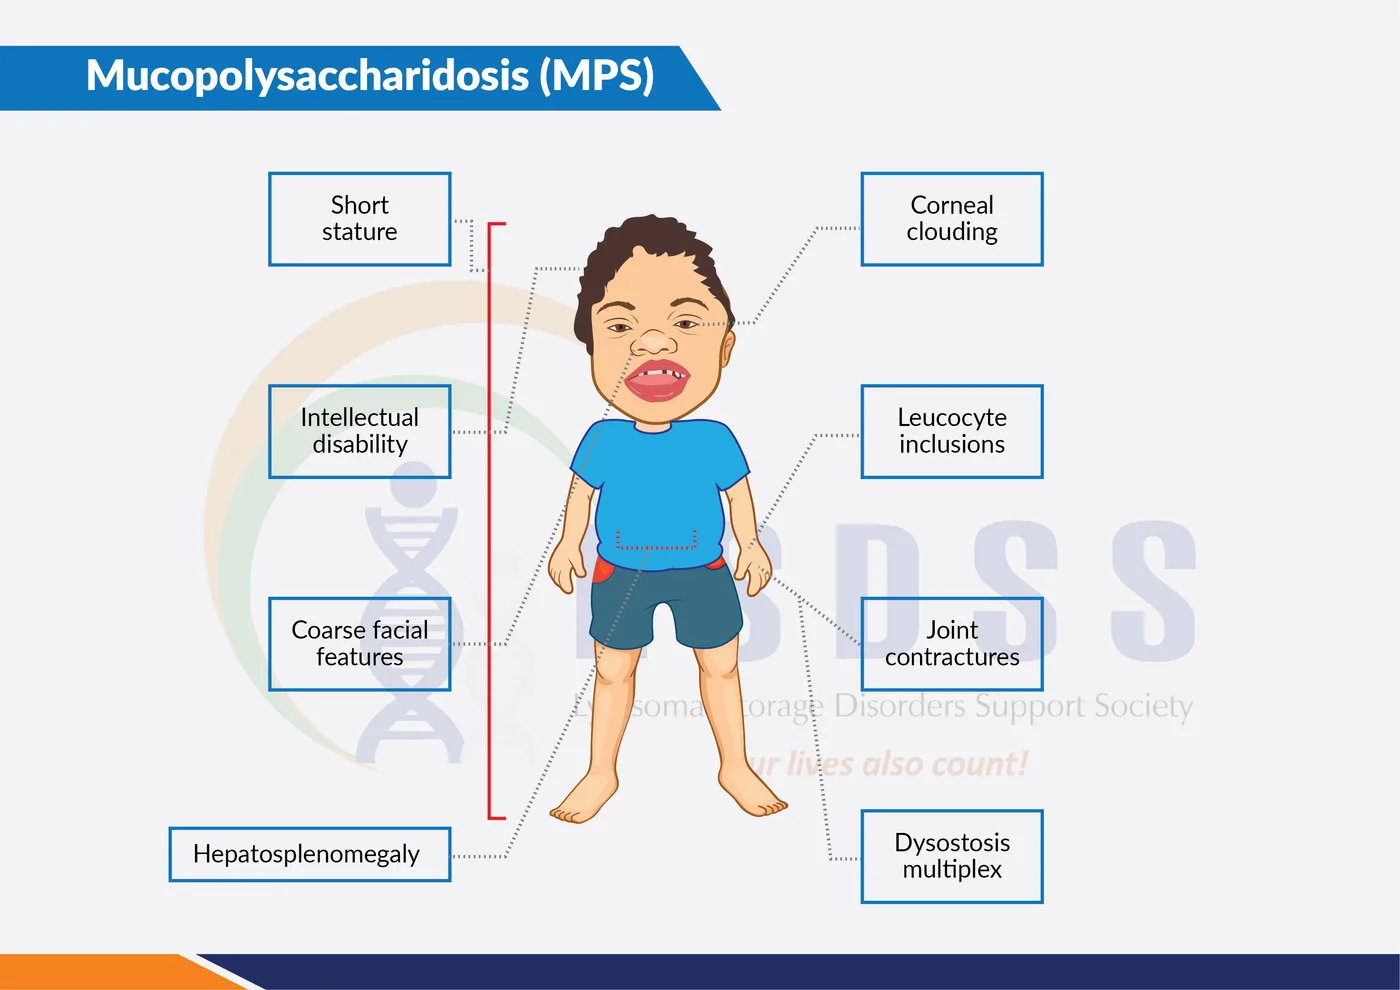
Symptoms depend on the type, but many children with MPS have:
- Coarse facial features, a large head and a large tongue
- Short stature and changes in the bones and spine
- Stiff joints and limited movement, or very loose joints in MPS IV
- Frequent colds, ear infections, noisy breathing and sleep apnoea
- An enlarged liver and spleen, and hernias near the belly button or groin
- Clouded corneas, hearing loss, heart valve problems and, in some types, developmental delay
When to see a doctor
Consult a doctor, ideally a geneticist or paediatrician, if your child has:
- Coarsening facial features or a large head
- Stiff joints, a curved back or short stature
- Repeated ear infections, noisy breathing or snoring
- Delayed development or loss of skills already learned
Because MPS affects many parts of the body, its signs are often treated separately. Ask about MPS if several of them appear together.
Causes
What causes MPS?
Each type of MPS is caused by changes (mutations) in a gene that gives the body instructions to make one of the enzymes needed to break down GAGs.
When the enzyme is missing or works poorly, GAGs build up inside lysosomes. Over time this damages cells and tissues throughout the body.
How it is inherited
- Most types of MPS are inherited in an autosomal recessive pattern.
- When both parents are healthy carriers, each pregnancy has a 1 in 4 (25%) chance of an affected child.
- MPS II (Hunter syndrome) is X-linked and is usually passed from a carrier mother to her son.
- Genetic counselling, carrier testing and prenatal testing can help families plan.
How is MPS diagnosed?
A combination of tests confirms MPS and identifies the type, which guides treatment.
01
Urine GAG test
A urine test that measures GAGs is often the first step. Raised levels suggest MPS, and the pattern can point to the type.
02
Enzyme test
A blood test, often on a dried blood spot, measures the activity of the MPS enzymes. Low activity of one enzyme confirms the type.
03
Genetic test
Confirms the gene change, can help predict severity in some types, and allows carrier and prenatal testing in the family.
04
Organ assessments
X-rays, MRI of the brain and spine, heart scans, hearing and eye tests, and sleep studies show how the disease is affecting the body.
Treatment for MPS
There is no cure yet, but treatment can slow the disease and improve quality of life. The right approach depends on the type and the child’s age.
Enzyme replacement therapy (ERT)
The missing enzyme is given as an intravenous infusion, usually every week, for life. ERT can improve breathing, walking, joint movement and the size of the liver and spleen. Standard ERT does not reach the brain, so it does not treat learning or behaviour problems.
Medicines include
- MPS I: laronidase (Aldurazyme®)
- MPS II: idursulfase (Elaprase®) or idursulfase beta (Hunterase®, approved in India in 2026)
- MPS IVA: elosulfase alfa (Vimizim®)
- MPS VI: galsulfase (Naglazyme®)
- MPS VII: vestronidase alfa (Mepsevii®)
Stem cell transplant (HSCT)
A bone marrow or cord blood transplant from a healthy donor can supply the missing enzyme throughout the body, including the brain. It is the preferred treatment for young children with severe MPS I (Hurler syndrome), ideally before about two years of age, and may be considered for some other types. Early diagnosis is essential for it to work.
Supportive and long-term care
Most patients need care from many specialists.
This can include
- Surgery for hernias, tonsils and adenoids, ear tubes, carpal tunnel or the spine
- Hearing aids and eye care
- Physiotherapy to keep joints moving
- Regular heart and breathing check-ups
People with MPS face a higher risk during anaesthesia because their airways can be narrow, so surgery should be planned at a centre experienced in MPS. For MPS II, tividenofusp alfa (Avlayah®) received accelerated approval in the US in March 2026 as the first enzyme therapy designed to reach the brain, for children whose neurological symptoms are not yet advanced; it is not yet approved in India. There is no approved treatment for MPS III yet, but gene therapies and other treatments are being studied in clinical trials.
Clinical trials and studies in India
Studies of mucopolysaccharidosis (MPS) that are recruiting, or about to recruit, in India. This list updates automatically every day.
There are no studies of mucopolysaccharidosis (MPS) recruiting in India at the moment. This list is checked every day, so new studies will appear here automatically.
Last checked 11 November 2026 on ClinicalTrials.gov. Always talk to your doctor before joining a study.
Accessing treatment in India
Getting treatment and financial support
Treatment for MPS is lifelong and expensive, costing from several lakhs to a few crore rupees a year. These are the main sources of help.
Government support (NPRD)
Several types of MPS are listed under the National Policy for Rare Diseases. Eligible patients can receive financial assistance of up to ₹50 lakh for treatment at a designated Centre of Excellence (COE).
- Visit your nearest COE with all medical reports
- Assistance is subject to approval
- The ₹50 lakh limit may not cover lifelong treatment
Other sources of help
- State government schemes
- Corporate social responsibility (CSR) funding
- Crowdfunding through the government rare disease portal
- Charitable access programmes (limited places)
How LSDSS helps
- Connects patients with COEs and specialists
- Guides families through funding applications
- Shares updates on support programmes
- Brings patients and caregivers together
Frequently asked questions
Answers to common questions about mucopolysaccharidosis (MPS).
Still have a question?
A group of rare inherited disorders in which the body lacks one of the enzymes needed to break down glycosaminoglycans (GAGs), long chains of sugar molecules. GAGs build up and damage the bones, joints, organs and, in some types, the brain.
Here, MPS stands for mucopolysaccharidosis (plural: mucopolysaccharidoses), a group of rare inherited lysosomal storage disorders. Its main types are known as MPS I, II, III, IV, VI, VII and IX. In other areas of medicine, the letters MPS can mean something else, such as myofascial pain syndrome.
There are seven main types: MPS I (Hurler, Hurler-Scheie and Scheie), MPS II (Hunter), MPS III (Sanfilippo), MPS IV (Morquio), MPS VI (Maroteaux-Lamy), MPS VII (Sly) and the extremely rare MPS IX. Several have subtypes.
Common signs include coarse facial features, short stature, bone and spine changes, stiff joints, an enlarged liver and spleen, hernias, frequent ear and chest infections, noisy breathing, clouded corneas, hearing loss and heart valve problems. Some types also cause developmental delay and behaviour problems.
It varies widely with the type and severity. Severe forms, such as untreated Hurler syndrome, the severe form of Hunter syndrome and Sanfilippo syndrome, often shorten life to childhood or the teenage years. People with milder forms can live into adulthood. Early treatment and good supportive care can improve both quality of life and survival.
Not yet. ERT is available for MPS I, II, IVA, VI and VII, and a stem cell transplant can help some children if it is done early. These treatments slow the disease but cannot reverse damage that has already happened, which is why early diagnosis matters.
It varies between countries. In many Asian countries, MPS II (Hunter syndrome) is the most commonly reported type.
Most types are autosomal recessive: a child is affected when both parents pass on a faulty copy of the gene. MPS II is X-linked and is usually passed from a carrier mother to her son. Genetic counselling can explain the risk for each family.
Mucolipidosis II and III are rare inherited disorders that look similar to MPS. They are caused by changes in the GNPTAB or GNPTG gene, which stop many enzymes reaching the lysosomes. ML II (I-cell disease) is severe and starts in infancy; ML III is milder and starts in childhood. There is no approved treatment, but supportive care helps.
First, visit your nearest Centre of Excellence (COE) with all medical reports, to be evaluated and enrolled on the Government of India’s rare disease portal for crowdfunding and CSR donations. Second, register with LSDSS for support and the latest information. A few companies have provided free treatment to some patients in India through charitable access programmes, but places are very limited.
Other lysosomal storage disorders
LSDSS supports patients and families living with all lysosomal storage disorders.
A fatty substance builds up in nerve cells of the brain and spinal cord.
Sulfatides build up and damage the protective covering of nerves.
A fatty substance builds up in nerve cells and, in babies, in other organs and bones.
Waste material builds up in nerve cells, causing seizures and loss of vision.
Living with MPS?
Register with LSDSS for treatment guidance, support and the latest updates. You are not alone.
This page is for general information and awareness only. It does not replace advice from a qualified doctor. Last reviewed: November 2026.